
HUDSON
BIOTECH
Tesamorelin Clinical Research Context and NCT07481734 Overview
An evidence-aware overview of tesamorelin, its FDA-approved indication, investigational liver-fat research, and the importance of cautious interpretation when referencing NCT07481734.
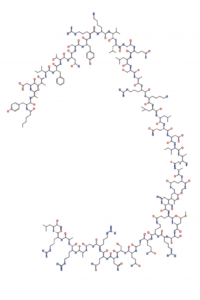
Tesamorelin is a synthetic GHRF/GHRH analog. In the U.S., FDA approval covers only excess abdominal fat reduction in adults with HIV-associated lipodystrophy.
Tesamorelin has investigational rationale in liver-fat research. Studies have reported reduced liver fat and less fibrosis progression in HIV-associated NAFLD.
What Tesamorelin Is
Tesamorelin is a synthetic GRF/GHRH analog that increases growth hormone and IGF-1 release. In the U.S., it is approved for reducing excess abdominal fat in adults with HIV-associated lipodystrophy.
Current labeling states that EGRIFTA WR 1.28 mg and EGRIFTA SV 1.4 mg have different dosing, reconstitution, and storage instructions.
Official Labeled Use Versus Investigational Liver-Fat Research
The approved-label story and the investigational liver-fat story are not the same.
Approved-Label Story
Tesamorelin’s approved-label context is HIV-associated lipodystrophy with excess abdominal fat. That is the official use framework and should not be blended with separate liver-disease research.
Investigational Liver-Fat Story
The liver-fat and fibrosis discussion comes from investigational research in hepatic fat fraction and fibrosis-related outcomes. This is scientifically relevant background, but it is not the same as an FDA-labeled MASLD or MASH indication.
Approved-Label Story
Tesamorelin’s approved-label context is HIV-associated lipodystrophy with excess abdominal fat. This should remain separate from liver-fat, fibrosis, MASLD, or MASH research discussions.
Investigational Liver-Fat Story
The liver-fat discussion is based on research involving hepatic fat fraction and fibrosis-related outcomes. It may support scientific context, but it should not be presented as the same as the approved-label use framework.
01 NIH-reported liver health measures +
In a placebo-controlled 12-month trial in people living with HIV and NAFLD, NIH reported that tesamorelin improved liver health measures, reduced hepatic fat fraction, normalized hepatic fat fraction in 35% of tesamorelin-treated participants versus 4% on placebo, and was associated with less onset or worsening of fibrosis.
02 Massachusetts General Hospital summary +
Massachusetts General Hospital later summarized the same work as showing about a 37% relative reduction in liver fat versus placebo over 12 months.
03 JCI Insight publication context +
A later JCI Insight paper stated that tesamorelin reduced liver fat and prevented fibrosis progression in HIV-associated NAFLD over one year, while also showing changes in hepatic gene pathways related to oxidative phosphorylation, inflammation, and tissue repair.

NCT07481734 is relevant to search intent.
ClinicalTrials.gov lists NCT07481734 as a Phase II placebo-controlled tesamorelin study for liver-fat reduction, with lifestyle counseling and MRI-PDFF change to Week 52 as the primary endpoint.
NCT07481734 should be referenced cautiously as a public listing.
Why Tesamorelin Research Planning Is Not a Routine Sourcing Task
Tesamorelin requires protocol-aligned planning around indication, dose, route, formulation, placebo matching, geography, visits, and documentation. This is especially important because marketed EGRIFTA dosing differs from the investigational 2 mg once-daily regimen listed for NCT07481734.
Start the Right Tesamorelin Conversation
For tesamorelin clinical research material, the first step should be a focused program discussion. This discussion should cover indication, protocol stage, dose, formulation, comparator strategy, geography, and startup timeline.
FAQ:
What is tesamorelin?
Tesamorelin is a synthetic analog of human growth hormone-releasing factor, also known as a growth hormone-releasing hormone analog. According to FDA labeling, it stimulates the GRF receptor, increases growth hormone secretion, and leads to downstream IGF-1 effects.
What is tesamorelin FDA-approved for in the United States?
Current FDA labeling for EGRIFTA WR and EGRIFTA SV limits tesamorelin’s approved use to one indication. Specifically, it covers reduction of excess abdominal fat in HIV-infected adults with lipodystrophy.
Is tesamorelin FDA-approved for MASLD or MASH?
No. The FDA labels reviewed here do not list MASLD or MASH as approved indications. Instead, the approved use is limited to excess abdominal fat in adults with HIV-associated lipodystrophy.
Is tesamorelin a weight-loss drug?
No. Official labeling states that tesamorelin is not indicated for weight management. Therefore, it should not be positioned as a weight-loss therapy.
Why is tesamorelin being studied in liver-fat research?
Earlier NIH- and Mass General-linked research in people living with HIV and NAFLD reported reduced liver fat and less fibrosis progression with tesamorelin compared with placebo. Therefore, these findings help explain why tesamorelin remains of investigational interest in liver-fat studies.
What does NCT07481734 describe?
Official ClinicalTrials.gov snippets describe NCT07481734 as a Phase II, randomized, double-blind, placebo-controlled study evaluating daily subcutaneous tesamorelin for liver-fat reduction. In addition, the record references MASLD or NAFLD, adults ages 18 to 75, standardized lifestyle counseling in both groups, and a primary MRI-PDFF endpoint at Week 52.
Why is NCT07481734 a compliance-sensitive reference?
Because the official record snippet includes “Mock Study” in the title, teams should verify it before using it as a live marketing proof point. The snippet also lists Hudson Biotech as both sponsor and responsible party, and it identifies a China site at Peking University Shenzhen Hospital.
Does NCT07481734 use the same dose as the current labeled tesamorelin products?
Not based on the sources reviewed here. The NCT07481734 snippet describes tesamorelin 2 mg subcutaneously once daily. In contrast, current FDA labels list 1.28 mg once daily for EGRIFTA WR and 1.4 mg once daily for EGRIFTA SV. Also, the labels state that the marketed formulations are not substitutable.
What should sponsors or CROs prepare before requesting tesamorelin clinical research material?
At a minimum, teams should define the indication, protocol stage, target dose, formulation, comparator or placebo needs, countries, sites, timeline, and startup documentation. As a result, early planning makes vendor discussions more precise and helps reduce avoidable delays.
Does this page describe commercial EGRIFTA distribution?
No. This draft focuses on clinical trial and clinical research use, not commercial branded-drug distribution. Therefore, Hudson Biotech should not claim commercial EGRIFTA supply unless that role has been verified and cleared for publication.
Who is this page for?
This page is intended for biotech and pharmaceutical sponsors, CROs, procurement teams, investigators, and research institutions. Specifically, it supports teams evaluating tesamorelin in a clinical research or study-planning context.
Should Hudson Biotech use “tesamorelin peptide manufacturer USA” on this page?
Only if Hudson has verified its current U.S. legal entity and operating location. However, the client brief says USA-based, and this review did not independently confirm that detail.